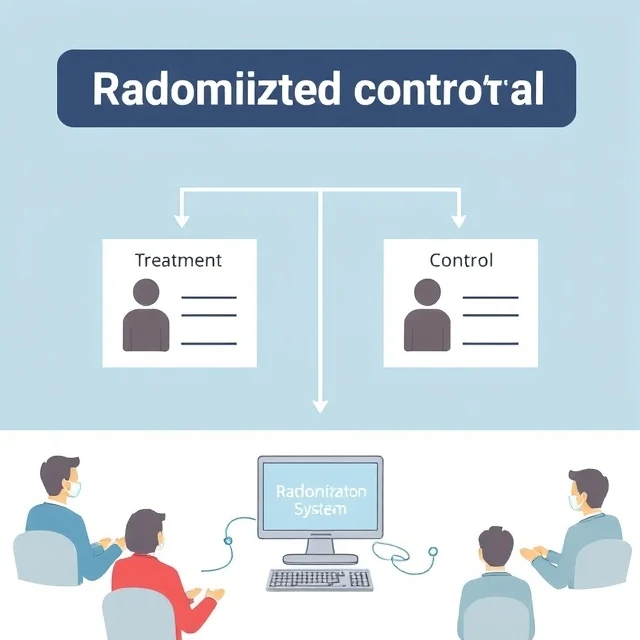
The randomized controlled trial is the gold standard for testing whether a treatment works. Participants are assigned to different groups by chance, usually through a computer-generated randomization sequence. One group gets the treatment, another gets a control, which may be a placebo or the standard treatment. Randomization ensures that known and unknown factors that could affect the outcome are distributed evenly between groups. Without it, differences between groups could be due to confounding rather than the treatment itself.
The design has several key features. Allocation concealment prevents researchers from knowing which group the next participant will be assigned to. Blinding, often double-blinding, keeps participants and researchers from knowing who gets what. Intention-to-treat analysis includes all participants in the groups they were assigned to, regardless of whether they completed the treatment, which preserves the benefits of randomization. The primary outcome is pre-specified, and the sample size is calculated to detect a clinically meaningful difference with adequate statistical power.
Key features:
- Randomization. Assignment by chance, not by choice.
- Control group. A comparison group receiving placebo or standard treatment.
- Blinding. Participants and researchers unaware of assignments.
- Intention-to-treat. All participants analyzed in their assigned groups.
- Pre-specified outcomes. Defined before the trial begins.
RCTs can be impractical for rare diseases, surgical procedures, or long-term outcomes. In those cases, observational studies provide complementary evidence.
Comments
No comments yet. Be the first to share a thought.
Leave a comment